A child with diabetes needs more than a prescription: diagnosis, insulin or other treatment, glucose monitoring, food planning, school coordination and age-appropriate support must work together. By the end, you will know what dedicated care includes, which benefits to expect, what families manage at home and how to judge whether a paediatric service is equipped to help.
Key takeaways
- Seek urgent care for vomiting, deep breathing, severe weakness or dehydration.
- Confirm the diabetes type before choosing long-term treatment.
- Create written plans for meals, medicines, glucose checks and school emergencies.
- Build independence gradually with supervision matched to your child’s age.
How early, accurate diagnosis changes a child’s care
Early, accurate diagnosis changes care by identifying the diabetes type and urgent metabolic risk before treatment is delayed. Excessive thirst, frequent urination, unexplained weight loss, fatigue, vomiting or dehydration need prompt assessment; vomiting, deep breathing, severe weakness or dehydration can signal diabetic ketoacidosis and require emergency care.
A dedicated paediatric assessment examines:
- Type 1 diabetes, including whether insulin is needed immediately
- Type 2 diabetes, while remembering that excess weight does not rule out type 1
- Monogenic diabetes or ketosis-prone or mixed presentations when the history and test results suggest them
- Blood glucose, ketones, HbA1c and signs of dehydration
- Associated conditions and future screening needs, based on the child’s age, diabetes duration and type
Correct classification prevents two serious errors: delaying insulin for a child with type 1 diabetes, or giving a child with type 2 diabetes an unnecessarily narrow treatment plan. It also creates a baseline for monitoring blood pressure, lipids, kidney health, eyes, thyroid function, coeliac disease and nerves when those checks become clinically appropriate.
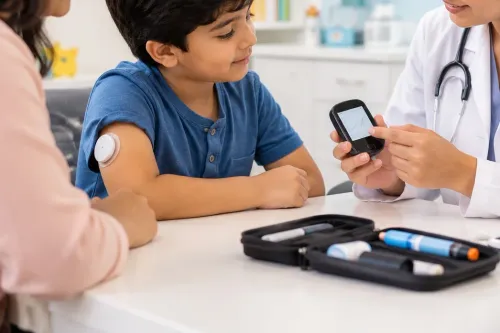
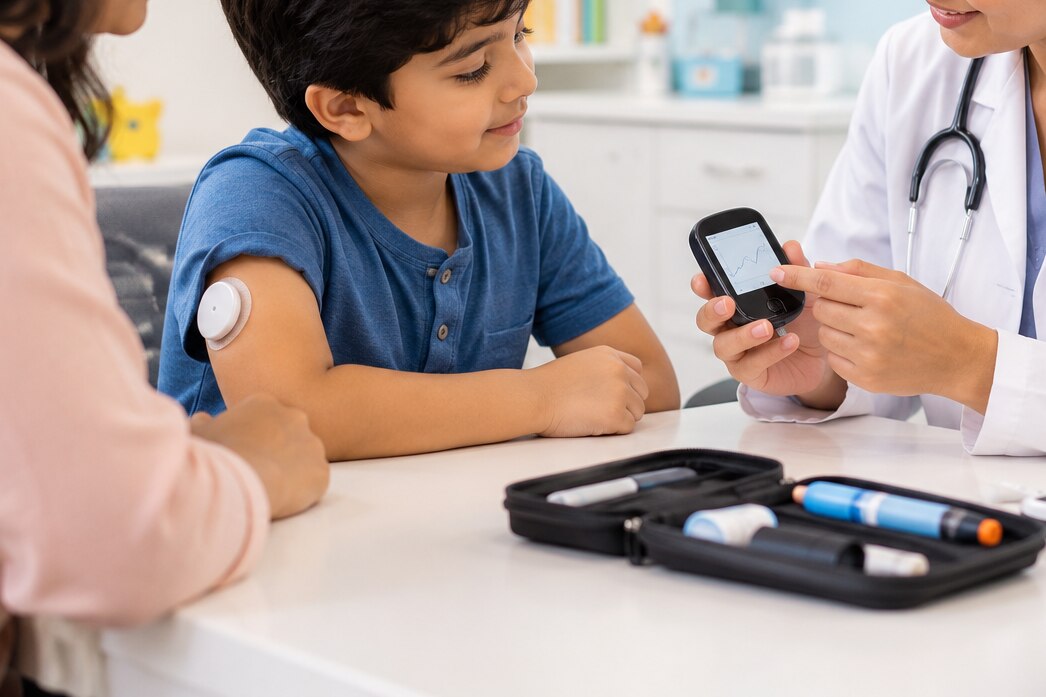
The benefits of children diabetes care extend beyond a prescription. An endocrinology clinician works with a diabetes educator, dietitian and psychosocial professional to connect insulin, food, exercise, school and family routines. The team provides structured education on glucose checks, carbohydrate estimation, hypoglycaemia treatment and sick-day rules, then revisits it as the child grows.
Early psychosocial screening can also uncover anxiety, diabetes distress, fear of low glucose or family conflict before these problems disrupt insulin use and glucose control.
What treatment looks like as children grow and change
Children diabetes treatment benefits are clearest when the plan changes with the child, rather than forcing the child to follow a fixed dose. Growth and puberty can raise insulin needs, while appetite and activity changes can quickly produce high or low glucose.
| Diabetes pattern | Treatment adaptation | Monitoring and review |
|---|---|---|
| Type 1 diabetes | Insulin remains essential; doses follow growth, meals, activity and illness | Glucose data guides adjustments; the usual HbA1c aim is below 7.0% when achievable without severe or frequent hypoglycaemia |
| Type 2 diabetes | Family-centred lifestyle support plus medication; metformin suits a metabolically stable child, while marked hyperglycaemia or ketosis may require insulin | Confirm the type before narrowing treatment, because obesity does not exclude type 1 diabetes |
| Uncertain or mixed presentation | Reassess for type 1, type 2, ketosis-prone or monogenic diabetes when findings do not fit | Review symptoms, ketones, glucose patterns and treatment response |
At every follow-up, the paediatric team revisits:
- Insulin amounts, injection technique, glucose meter or sensor data and the child’s HbA1c goal.
- Meal planning that fits appetite, family foods and sports instead of imposing a rigid diet.
- Education on hypoglycaemia treatment, sick-day rules and diabetic ketoacidosis prevention.
- School instructions for glucose checks, insulin, exercise, food, emergency glucagon and illness.
Education starts at diagnosis and returns whenever the child’s routine or responsibilities change. A diabetes educator, dietitian and psychosocial professional help connect medical decisions with family life, school hours and growing independence.
How families, schools and children handle diabetes safely each day
Effective child diabetes management care starts with one written plan shared by caregivers, the child, school staff and childcare providers. It should state glucose-check times, insulin doses, carbohydrate estimates, hypoglycaemia treatment, sports adjustments, sick-day actions and emergency contacts.
- Keep glucose meter or continuous glucose monitor supplies, insulin, fast-acting glucose and a written care plan accessible during school hours.
- Train designated staff to recognise hypoglycaemia, give glucose promptly and use prescribed glucagon when the child cannot safely swallow or becomes unconscious.
- Before sports, check the child’s glucose according to the clinical plan, carry fast-acting carbohydrate and recheck after prolonged or intense activity.
- During illness, follow the written sick-day instructions for glucose, fluids, insulin and ketone checks; never stop insulin in a child with type 1 diabetes without medical advice.
- Tell teachers and coaches what symptoms require action, who holds supplies and when parents or the diabetes team must be called.
Review the plan after a severe low, repeated highs, vomiting, a change in sports or a new school timetable. Recurrent vomiting, dehydration, breathing difficulty or suspected ketones needs urgent medical assessment, not trial-and-error dose changes at home.
Responsibility should move gradually. Caregivers can ask the child to check glucose, count carbohydrates or prepare supplies while an adult verifies the dose. A paediatric team should also screen for diabetes distress, anxiety, fear of hypoglycaemia and family conflict, then arrange support when concerns affect daily care.
Why emotional support and gradual independence affect outcomes
Emotional support belongs in routine diabetes care because distress, anxiety, low mood, fear of hypoglycaemia and family conflict can disrupt insulin use and glucose management. A diabetes team should screen for these concerns during reviews, explain the findings without blame, and arrange timely psychological or social support when needed.
Pediatric diabetes support is clinical care, not an optional counselling extra.
Responsibility should move gradually from caregiver to child, guided by development rather than age alone. Young children may help choose a sensor site or tell an adult how they feel, while older children can practise checking glucose and preparing supplies with supervision.
Adolescents need privacy and respect, but removing oversight suddenly can lead to missed doses, unrecognised hypoglycaemia or unsafe sick-day decisions.
Before handing over a task, the team should check whether the child can do it reliably, explain when help is needed, and repeat the assessment as puberty, school demands and treatment change. Independence should remain shared until the young person can:
- Monitor glucose and respond to unusual readings
- Calculate and give the prescribed dose safely
- Recognise and treat hypoglycaemia
- Follow the illness plan and obtain supplies
- Tell caregivers, school staff or clinicians when something is wrong
Caregivers also need support to replace constant checking with agreed routines, while siblings and school staff receive clear boundaries. A written plan, regular psychosocial screening and a planned transition to adult care protect relationships as well as health.
How to decide whether a dedicated paediatric service is right for your child
Choose a service for what it provides between appointments, not for the word “paediatric” on its sign. Advanced Diabetes & Weight Loss Clinic in Navi Mumbai can be one option to assess against these practical questions.
- Does a clinician experienced in childhood Type 1, Type 2 and, when indicated, monogenic diabetes review your child?
- Will you receive a written plan for hypoglycaemia, glucagon, illness, sports, school and sleepovers?
- Can the service offer rapid advice during vomiting, suspected ketones, glucose emergencies or device failure?
- Does it screen for blood pressure, lipids, kidney, eye, thyroid, coeliac and nerve problems at the appropriate age and diabetes duration?
- Does it address diabetes distress, anxiety, eating concerns and family conflict, with referral when screening identifies a problem?
- For Type 2 diabetes, does the plan combine family-centred lifestyle care with medication when indicated rather than treating diabetes as a weight-loss programme?
| Feature | Dedicated paediatric service | General or adult clinic |
|---|---|---|
| Developmental care | Adjusts teaching and responsibility for age and puberty | May place adult-style tasks on the child |
| Safety planning | Supplies written emergency and school instructions | Advice may remain verbal or generic |
| Follow-up | Coordinates educators, psychosocial care and screening | Care may focus mainly on glucose readings |
| Transition | Tests skills before transferring responsibility | Handover may happen by age alone |
Recurrent vomiting, dehydration, breathing difficulty or suspected ketones needs urgent medical assessment, not trial-and-error dose changes at home. Ask for a sample care plan before choosing.
Related service
Children Diabetes Care focuses on the early diagnosis, treatment, and long-term management of diabetes in kids and teenagers. Dr. View service → |
Frequently asked questions
How does early diabetes diagnosis change a child’s care?
It identifies the diabetes type and urgent metabolic risks, allowing treatment to start before dehydration or diabetic ketoacidosis worsens.
What does diabetes treatment look like as children grow?
Treatment changes with growth, puberty, activity, appetite, school routines and the child’s ability to manage glucose checks and medicines.
How can families and schools manage childhood diabetes safely?
Use a written plan covering glucose checks, meals, medicines, exercise, low blood glucose treatment and emergency contacts, then share it with trained school staff.
When is a dedicated paediatric diabetes service suitable?
Consider one when your child needs age-specific diagnosis, treatment adjustments, school coordination, emotional support or a gradual plan for self-management.
Keywords